
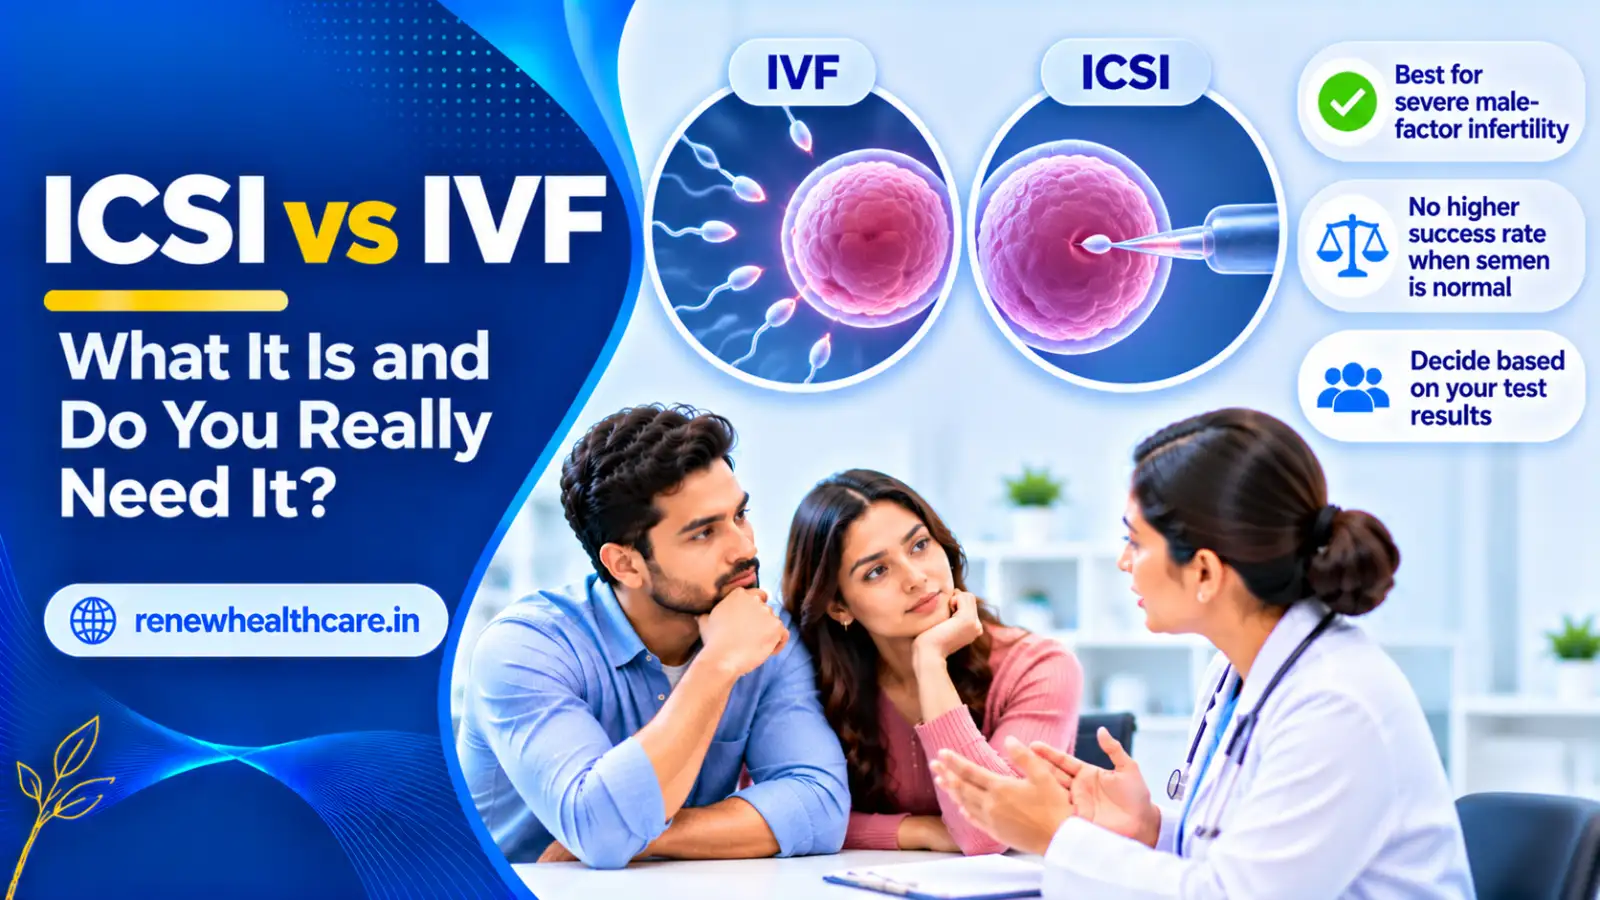
If your fertility treatment plan includes ICSI, you may be wondering whether it is genuinely necessary or simply an additional step in your IVF cycle.
ICSI stands for intracytoplasmic sperm injection. It is a laboratory procedure in which an embryologist injects one sperm directly into an egg. In conventional IVF, eggs and sperm are placed together in a laboratory dish, allowing fertilisation to occur without injecting the sperm.
ICSI is a well-established option for severe male-factor infertility and certain other situations, including previous fertilisation failure. However, when semen parameters are normal, research has not demonstrated a better live-birth rate with routine ICSI compared with conventional IVF.
The important question is not whether ICSI is more advanced, but whether your medical results provide a reason to use it.
What is the difference between IVF and ICSI?
Both conventional IVF and ICSI are performed as part of an IVF treatment cycle. The main difference is how fertilisation takes place in the laboratory.
Conventional IVF: Eggs and sperm are placed together in a laboratory dish. Sperm must reach and fertilise the egg without direct injection.
ICSI: An embryologist selects a sperm and injects it directly into an egg using specialised laboratory equipment.
ICSI is an additional laboratory procedure within the IVF cycle. It does not replace the other stages of IVF, such as ovarian stimulation, egg collection, embryo development and embryo transfer.
You can read more about what intracytoplasmic sperm injection involves.
Who may benefit from ICSI?
ICSI has an established role in selected fertility situations. Its use should be based on the couple's investigation results and treatment history.
| Situation | Is ICSI supported? |
|---|---|
| Severe male-factor infertility | Yes, an established indication |
| Sperm collected surgically | Yes, an established indication |
| Low or failed fertilisation in an earlier conventional IVF cycle | Reasonable to consider |
| Previously frozen eggs being used | Commonly used practice, although supporting data are limited |
| Embryo testing for a single-gene condition | May be used to avoid other sperm affecting the test |
| Unexplained infertility without a male factor | Not routinely recommended |
| Low egg numbers alone | Not a sufficient reason by itself |
| Older maternal age alone | Not a sufficient reason by itself |
| Chromosome screening of embryos alone | Not a sufficient reason by itself |
ICSI for severe male-factor infertility
ICSI is particularly useful when sperm-related problems make conventional fertilisation difficult.
This may include severe abnormalities in semen parameters or situations where sperm have been collected surgically rather than obtained through a regular semen sample.
The term severe male-factor infertility does not have one universally applied numerical cut-off across all studies. Different clinical trials have used different definitions. The treating specialist should explain which findings in your report support the recommendation.
For information about surgically collected sperm, read about sperm extraction procedures in azoospermia.
ICSI after previous fertilisation failure
If a previous conventional IVF cycle resulted in very low fertilisation or no fertilisation, ICSI may be considered in a subsequent cycle.
The reasoning is different from using ICSI routinely in every patient. A previous fertilisation problem provides a specific treatment-history reason to discuss changing the fertilisation method.
ICSI when frozen eggs are used
ICSI is commonly used when previously frozen eggs are thawed for treatment, although the evidence supporting this practice is limited.
The decision should still be discussed with the fertility team in the context of the treatment plan.
ICSI and genetic testing of embryos
ICSI may be used in certain embryo-testing situations, particularly when testing for a single-gene condition, to reduce the possibility of stray sperm affecting the test.
However, embryo chromosome screening alone is not a reason to assume that ICSI is necessary.
You can learn more about genetic testing in IVF and PGT-A and embryo genetic screening.
Does ICSI improve IVF success when sperm parameters are normal?
This is one of the most important questions to discuss before agreeing to ICSI.
Research comparing ICSI with conventional IVF in couples without severe male-factor infertility has not demonstrated a clear improvement in live-birth outcomes from routinely using ICSI.
A 2026 pooled analysis of six randomised trials reported:
| Outcome | ICSI | Conventional IVF |
|---|---|---|
| Live birth per couple | 32.8% | 34.5% |
| Cumulative live birth | 43.2% | 47.4% |
For live birth per couple, the relative risk was 0.96, with a 95% confidence interval of 0.85 to 1.09. For cumulative live birth, the relative risk was 0.92, with a confidence interval of 0.84 to 1.01.
These findings did not establish a live-birth advantage for ICSI in the studied population.
A Cochrane review of couples with normal sperm count and motility also did not establish a clear live-birth benefit. The certainty of evidence was low, and some of the studies overlap with the later pooled analysis, so these results should not be treated as independent evidence.
What do major fertility guidelines recommend?
Several major organisations have reached similar conclusions about routine ICSI when there is no male-factor indication.
NICE (2026): Advises against using ICSI for non-male-factor fertility problems when semen parameters are normal.
ESHRE (2023): Does not recommend ICSI over conventional IVF for unexplained infertility.
ASRM (2026): Does not recommend routine ICSI for non-male-factor infertility.
WHO (2025): Recommends IVF alone rather than IVF with ICSI for unexplained infertility after unsuccessful stimulated IUI.
The WHO recommendation is specific to unexplained infertility after unsuccessful stimulated IUI. It should not be interpreted as a recommendation against ICSI for severe male-factor infertility.
Some studies have reported higher fertilisation rates with ICSI in unexplained infertility. However, an improvement in fertilisation does not automatically translate into more live births.
For example, a randomised trial involving 1,064 couples found a live-birth rate after the first embryo transfer of 35% with ICSI and 31% with conventional IVF. The difference was not statistically significant. Fertilisation failure was also not significantly different.
The evidence therefore does not support assuming that ICSI is better simply because it involves direct sperm injection.
Are there risks associated with ICSI?
ICSI requires additional laboratory time, staff and technical expertise. It also increases the cost of an IVF cycle.
Another question couples commonly ask is whether ICSI affects the health of children born after treatment.
The available evidence is complicated because studies cannot always separate the possible effects of the procedure from the underlying infertility, genetic factors and parental characteristics.
What does research say about birth defects?
Some observational studies have reported a small increase in birth defects associated with ICSI. However, the findings do not establish that ICSI itself is the cause.
For example, a South Australian study reported birth defects diagnosed before the age of five in:
9.9% of ICSI pregnancies
7.2% of conventional IVF pregnancies
5.8% of pregnancies without assisted conception
After statistical adjustment, the association remained for ICSI compared with pregnancies without assisted conception. However, the researchers could not exclude residual confounding, and infertility itself was also associated with birth defects.
Another large study combined IVF and ICSI rather than separating the two procedures, so its findings cannot establish an ICSI-specific risk.
What about children's long-term development?
A pooled analysis of 13 studies reported an association between ICSI and autism, with a relative risk of 1.36. However, the evidence was graded as low certainty.
The same analysis did not find clear differences for ADHD, intellectual disability or cerebral palsy.
These findings are not proof that ICSI causes developmental conditions. More research is needed to understand the role of the treatment, parental factors and underlying infertility.
A 2026 pooled analysis of randomised trials reported birth defects in 0.7% of the ICSI group and 1.1% of the conventional IVF group. However, the trials were not adequately powered to detect differences in birth defects.
The practical takeaway: A possible small difference in risk cannot be ruled out, but its cause is not established. Where ICSI has a clear medical indication, the potential benefits should be considered alongside the uncertainties. Where there is no demonstrated benefit, adding an extra procedure deserves careful discussion.
When is ICSI needed, and when should you question it?
Before agreeing to ICSI, it helps to understand why it has been included in your treatment plan.
ICSI may be reasonable when:
The semen analysis shows severe male-factor abnormalities.
Sperm have been collected surgically.
A previous conventional IVF cycle resulted in low or failed fertilisation.
Previously frozen eggs are being used.
Embryo testing for a single-gene condition is planned and the laboratory has a reason to use ICSI.
ICSI is not routinely needed when:
Semen parameters are normal and there is no history of fertilisation failure.
Sperm parameters are only mildly reduced without another specific indication.
The only concern is a low number of eggs.
The only concern is older maternal age.
The only proposed reason is chromosome screening of embryos.
If ICSI is being recommended for every couple by default, ask the fertility team to explain the medical reason. The ESHRE add-ons guidance also cautions against using ICSI for all couples irrespective of their investigation results, particularly when additional costs are charged.
What should you ask your fertility specialist before choosing ICSI?
You should understand why a particular fertilisation method is being recommended before proceeding with treatment.
Consider asking:
Which result in our semen analysis makes ICSI necessary?
Is there a specific male-factor problem, or is our infertility unexplained?
Did a previous IVF cycle show low or failed fertilisation?
Would conventional IVF be a reasonable option in our situation?
What are the additional laboratory charges for ICSI?
What does the available evidence say about live-birth outcomes for couples with our clinical findings?
The most useful question is:
“Which of our results makes ICSI necessary, and what is the plan if we use conventional IVF?”
You can also read questions to ask your IVF doctor before starting treatment.
Frequently asked questions
What is the difference between IVF and ICSI?
In conventional IVF, eggs and sperm are placed together in a laboratory dish, allowing fertilisation to occur naturally. In ICSI, an embryologist injects one sperm directly into each egg. ICSI is an additional laboratory procedure within an IVF cycle.
Do I need ICSI if my semen report is normal?
Not usually. Research has not established a better live-birth rate with routine ICSI in couples without severe male-factor infertility. NICE, ESHRE and ASRM advise against routine use when there is no male-factor indication. A previous cycle with low or failed fertilisation is a different situation and may justify considering ICSI.
You can learn more about how to read a semen analysis report.
Is ICSI better than conventional IVF?
Neither method is automatically better for every couple. ICSI has an established role in severe male-factor infertility and selected treatment situations. When semen parameters are normal, trials have not demonstrated a clear live-birth advantage from routine ICSI.
Are children born after ICSI healthy?
Most available evidence is observational and cannot always separate the effects of ICSI from underlying infertility and parental factors. Some studies report possible associations with birth defects or certain developmental outcomes, but the evidence has important limitations. Discuss the risks relevant to your circumstances with your specialist.
Is ICSI used only for male infertility?
No. It is also used in selected situations involving previous fertilisation failure, surgically collected sperm, frozen eggs and certain single-gene embryo-testing procedures. However, using ICSI routinely for every couple without a specific indication is not supported by current major guidelines.
How much does ICSI cost?
ICSI requires additional laboratory time, staff and expertise, and it can increase the overall cost of IVF. The additional amount varies by clinic and treatment plan. Ask for an itemised estimate showing whether ICSI is charged separately from the IVF cycle and what each charge covers.
The bottom line
ICSI is an established fertilisation technique that can be valuable when sperm-related problems are severe, sperm are collected surgically or a previous conventional IVF cycle has resulted in poor fertilisation.
However, it is not automatically necessary for every IVF patient. When semen parameters are normal and there is no previous fertilisation failure, research has not demonstrated a clear improvement in live-birth rates with routine ICSI.
The decision should be based on your semen analysis, previous treatment history, planned embryo testing and the reproductive health of both partners.
Before agreeing to an additional procedure, ask your fertility specialist to explain the specific medical reason for recommending it.
Medical Review
Medically reviewed by Dr. Arnab Kundu.
View Dr. Arnab Kundu's profile at Renew Healthcare.
This article is intended for general educational purposes and does not replace individual medical advice. Please consult a qualified specialist about your own situation.